Explore

Need help with your project?
Oops! Something went wrong while submitting the form.
As an impact of the pandemic, self-care has become even more popular and omnipresent in 2026. Now, everyone knows that mental health is important, but with a busy life, work, daily commute, and family, it is difficult to find time to drive to a therapy session or attend a wellness retreat. So, the demand for digital solutions is growing rapidly. How to develop a mental health app that would be effective and relevant to current trends? Let’s discuss it!
In this article, we’ll address what types of general mental health apps exist, how the platform can be monetized, and what key features you need. Also, as a bonus, we will provide costs and timeframe for similar projects.

A mental health app is a digital health product that provides mental health support. It can guide exercises, help users monitor changes, connect them with professionals, or coordinate care.
The product model determines which health data it handles. Examples include mood entries, assessment responses, therapy notes, and session records. The app can support prevention and ongoing care, but it does not automatically replace diagnosis or treatment by a licensed professional.
Mental health apps can help people manage mental health issues and find mental health resources within the app. The app may become part of mental health care when it connects a patient with mental health services for a diagnosed mental disorder. That boundary affects claims, escalation, and whether the product is positioned for mental wellness or clinical care.
Mental health solutions include apps in several niches: online therapy sessions, relaxation, mood tracking, meditation, or breathing exercises
In terms of design and interface, the platforms can look very different and have a diverse set of features, depending on the final goals and target audiences. So, if you plan to create a mental health app, there is no pattern you can follow — UI/UX design, functionality, user flow, etc. will depend on your niche.
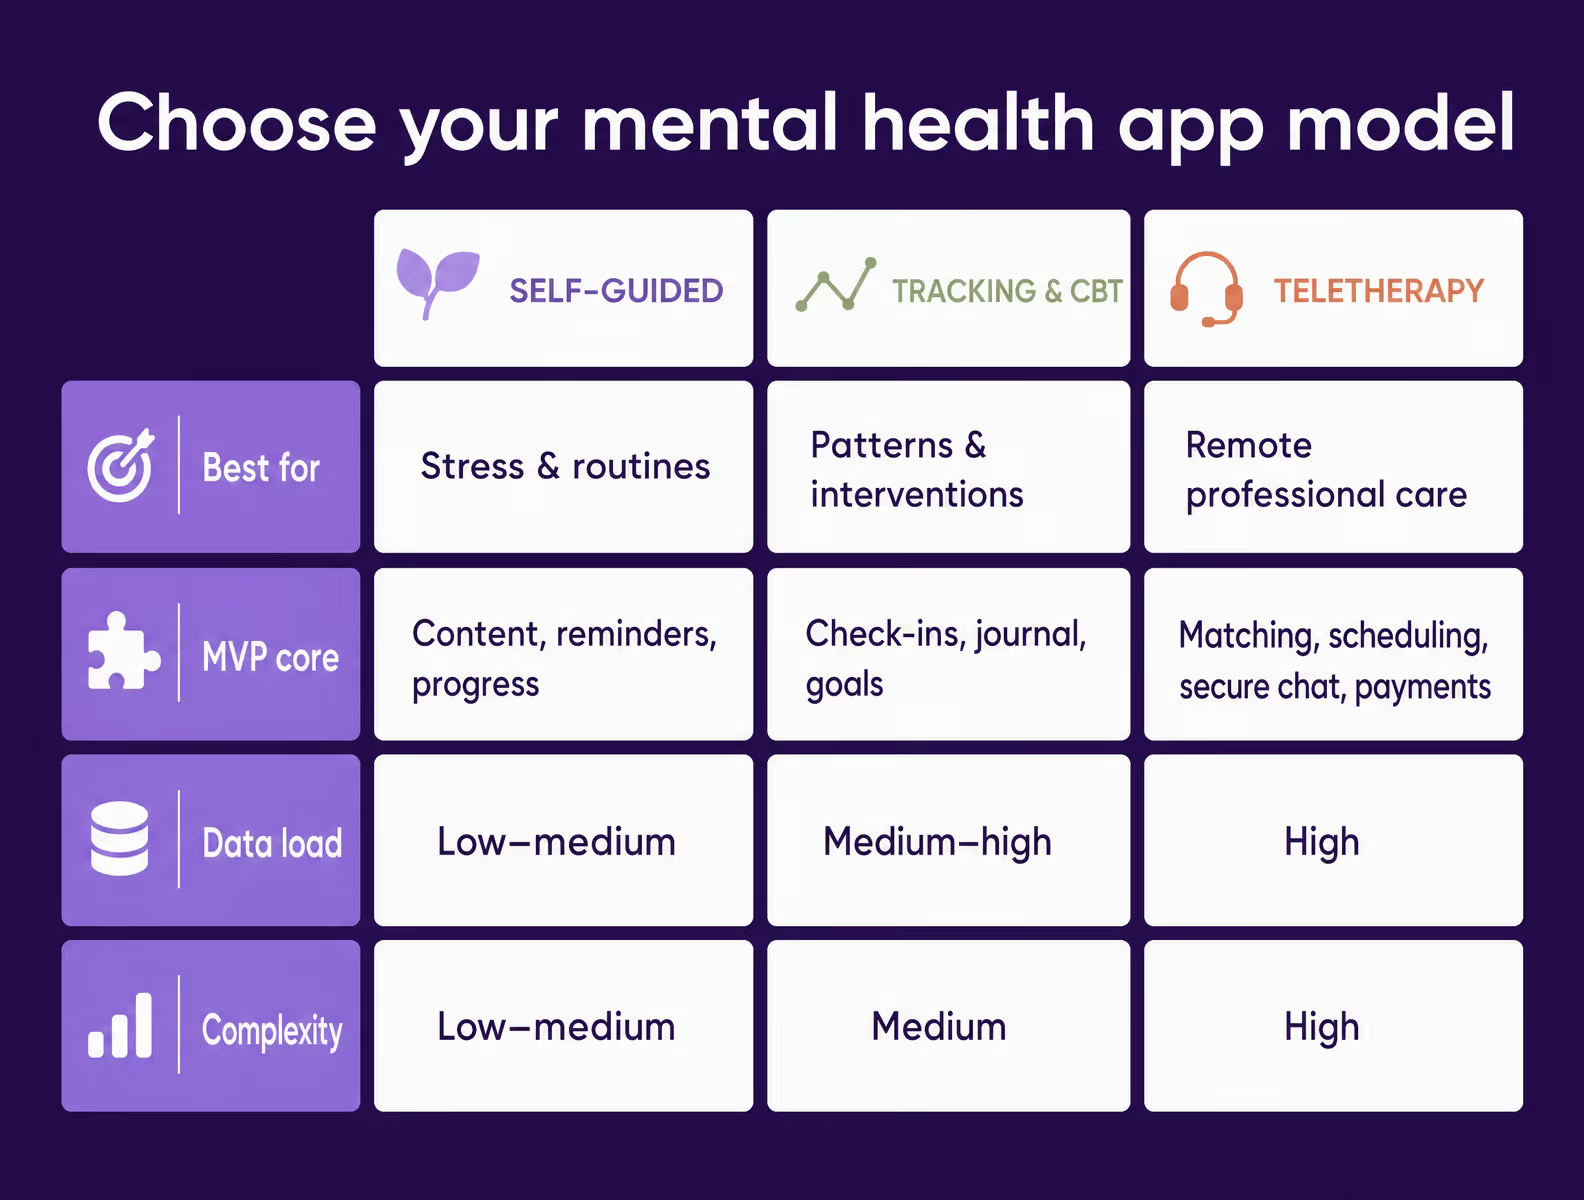
The product model sets boundaries for features, health data, and regulatory work. Self-guided products have a different risk profile from platforms that store therapy notes or connect users with licensed professionals.
| App type | Core user job | MVP features | Data and compliance load | MVP complexity |
| Self-guided wellness and meditation | Reduce stress and build routines | Content, reminders, favorites, progress | Lower without clinical relationships or protected health information. Privacy rules still apply | Low to medium |
| Mood, symptom, journaling, or CBT support | Track patterns and practice interventions | Check-ins, journal, assessments, goals | Medium to high because entries contain sensitive health data | Medium |
| Teletherapy and care coordination | Find a professional and receive remote care | Matching, scheduling, secure communication, payments | High because care workflows require consent, access controls, and audit logs | High |
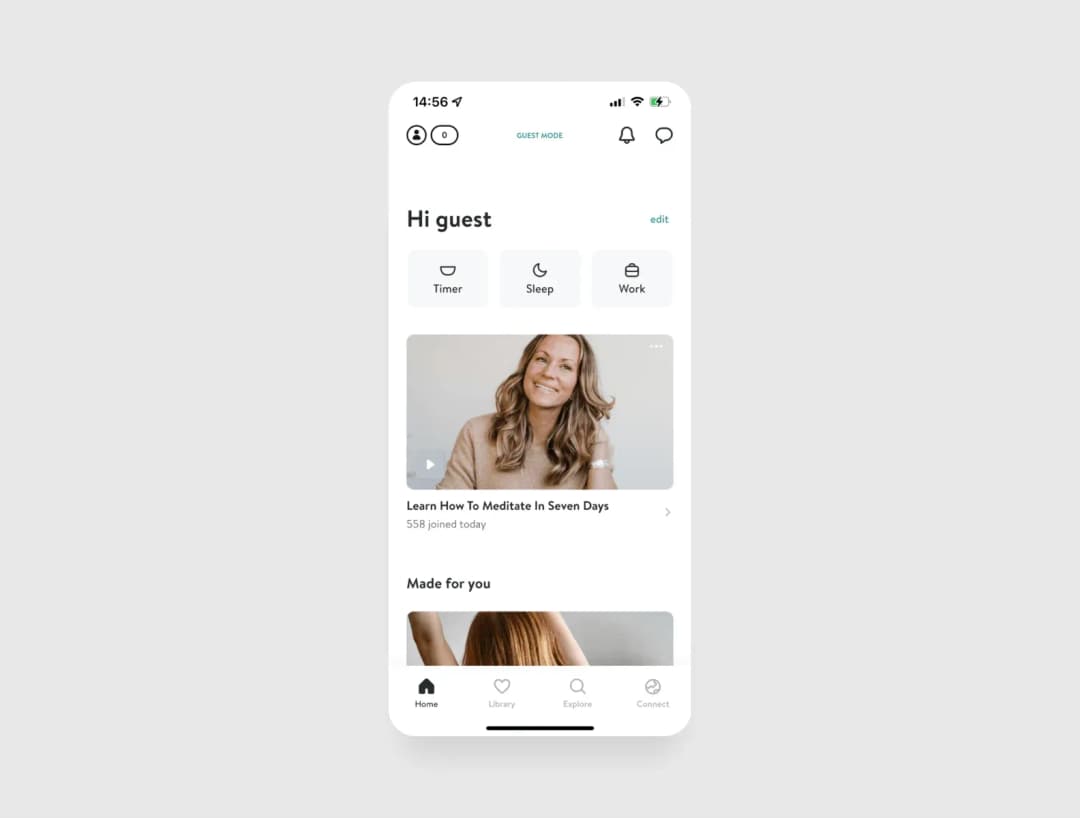
These self-guided mental health apps use breathing, meditation, or sleep content to build routines. A focused MVP combines content with reminders and progress tracking. Our meditation app development guide examines this model.
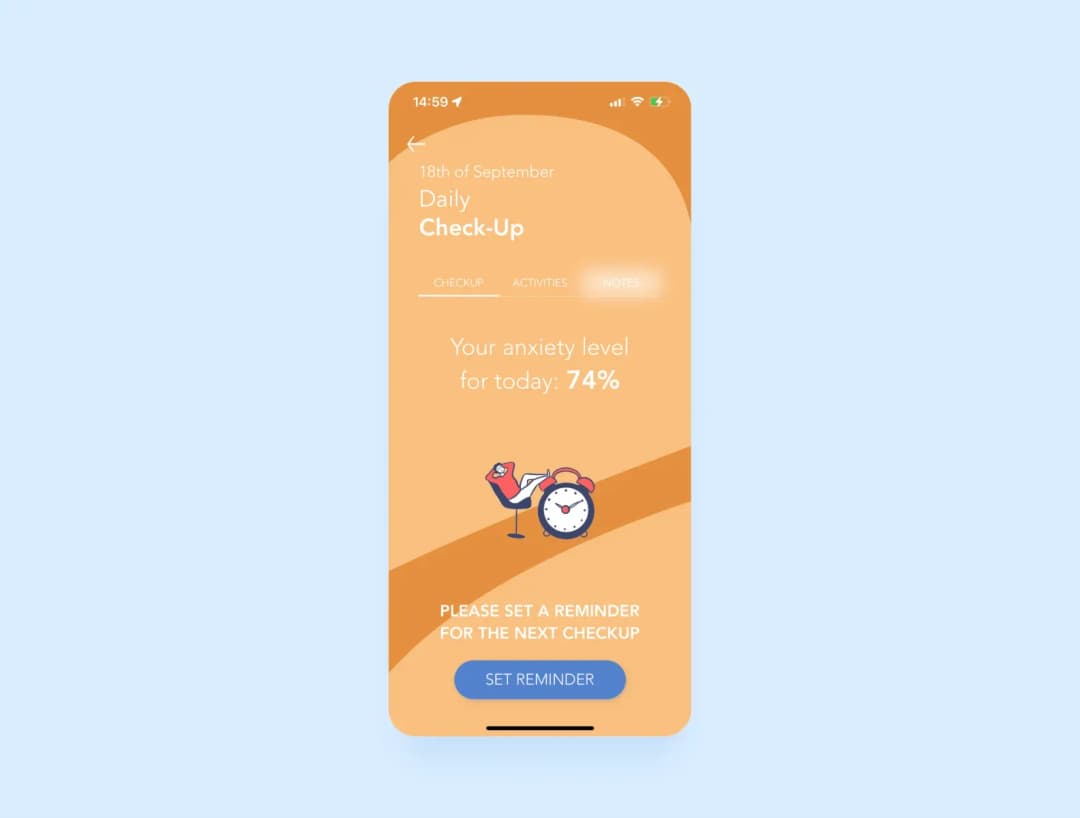
Tracking mental health apps record mood, symptoms, habits, or journal entries. Users can review patterns themselves or with a mental health professional. These insights must not read as an unvalidated diagnosis.
A mental health therapy app connects users with professionals through matching, scheduling, messaging, or video. Separate client and clinician workflows, along with sensitive records, increase compliance work.
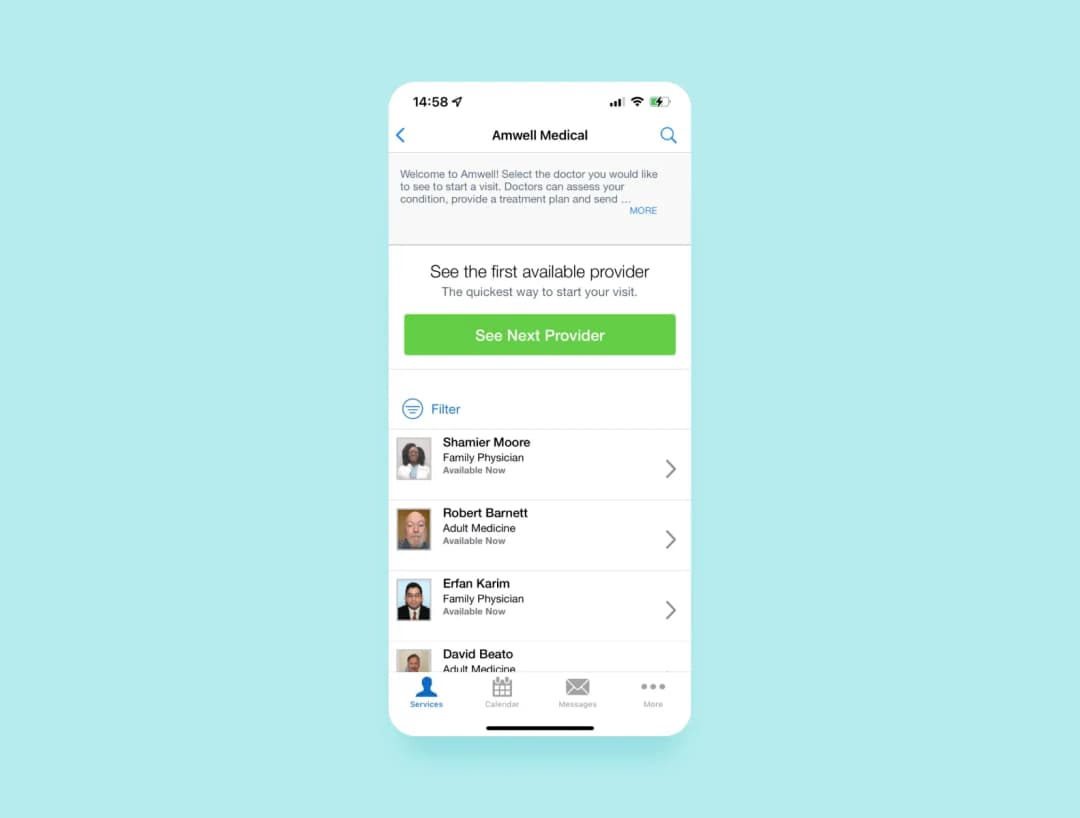
Teletherapy apps reduce practical barriers such as travel and limited local availability. They connect users with licensed professionals through scheduled audio or video sessions. The product complements clinical care rather than replacing every in-person assessment, treatment pathway, or crisis service.
For users, a focused app reduces friction around regular mental health support. It can combine check-ins, guided exercises, remote sessions, and follow-up tools in one accessible flow. This makes routine support easier to reach, while clear product limits keep the app from promising treatment it cannot provide.
For a product team or healthcare provider, digital delivery creates useful touchpoints between appointments and beyond a single physical location. Consented usage data also shows which flows people return to and where they stop. The business value comes from trust, retention, and one well-defined outcome rather than market size alone.
More than one billion people live with mental health conditions, while access to appropriate support remains insufficient. Digital products can reduce some access barriers, but the category is already crowded. Evidence quality, privacy practices, and clinical involvement differ widely between products.
Demand alone does not validate a mental health application. A new product needs one clear user job, a defined health data boundary, and a credible reason for people to return. This makes product scope more useful than another market forecast. Teams can evaluate a concept through the problem it solves, the level of care it supports, and the safeguards required for that model.
In 2026, many mental health apps compete on narrower use cases, from mindfulness and anxiety support to clinician-led care. Mental health apps that scale still need evidence that the core flow helps their audience.
A successful mental health app needs evidence that its core flow is an effective mental health intervention, not a larger feature list. Mobile app development choices also affect scalability as usage, content, or provider networks grow.
The business model works best when it follows the product’s value cycle and care journey. A self-guided wellness app and a teletherapy marketplace solve different problems, so they do not need the same payment structure.
Trust limits which monetization strategies fit mental health products. Pricing and renewal terms need to be clear. Advertising based on sensitive health data creates privacy and reputation risks, even when it generates short-term revenue.
BetterHelp, Headspace, and MindDoc represent three different product models rather than a ranking. Their feature sets show how care delivery, guided content, and self-monitoring lead to different user flows and revenue models. Exact prices and reach figures change too often to guide an evergreen product decision.

BetterHelp connects users with licensed therapists through messaging, audio, and video sessions. It uses a recurring subscription whose conditions vary by location, therapist availability, and plan terms.

Headspace focuses on guided meditation, sleep, and stress-management content. Its core consumer model is a subscription, while organizational plans extend the product to employers and other groups.

MindDoc combines mood tracking, journaling, progress patterns, and guided exercises. The product uses a freemium structure with paid subscription features, without relying on one fixed price across platforms and regions.
The core feature set depends on the product model. Most mental health apps still need secure onboarding, a primary support flow, progress feedback, a crisis pathway, accessibility, and privacy controls. Teletherapy products add provider workflows and secure communication.
| Capability | Why it matters | MVP implementation | Safety and privacy note |
| Secure onboarding and consent | Sets expectations before data collection | Account, consent, age, region | Collect only necessary data after consent |
| Mood, symptom, or journal tracking | Creates history and progress patterns | Check-ins, notes, trend chart | Treat entries as sensitive health data |
| Guided interventions and content | Gives users an immediate support flow | Exercises, breathing, meditation | Review clinical claims and evidence |
| Provider discovery and scheduling | Supports teletherapy journeys | Profiles, availability, booking | Verify credentials and control visibility |
| Secure messaging and video | Enables remote care | Chat, video, file sharing | Define retention, access, and audit rules |
| Progress dashboard and goals | Makes activity visible over time | Trends, goals, sharing controls | Avoid unvalidated diagnostic conclusions |
| Crisis support and escalation | Provides a route beyond self-service | Resources and human escalation | Never present automation as emergency care |
| Accessibility and localization | Reduces barriers for vulnerable users | Labels, captions, contrast, locales | Test with users and assistive technology |
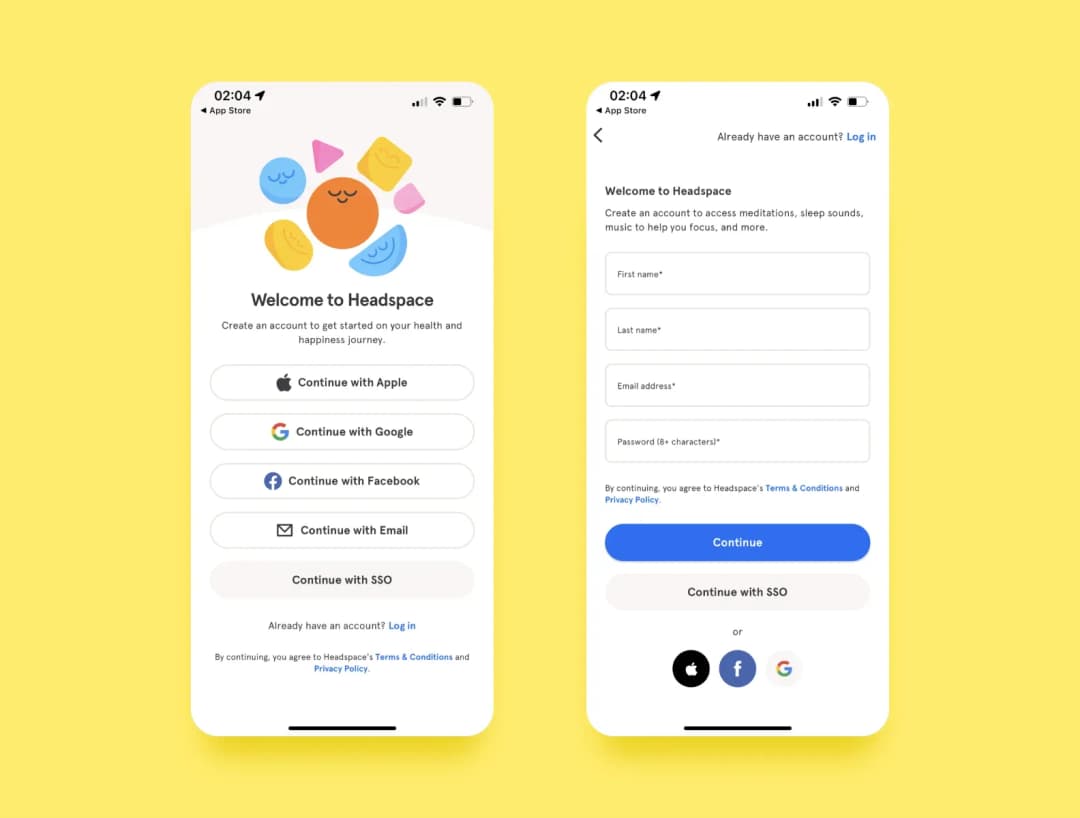
Onboarding explains what the app does, which information it collects, and where its limits begin. The flow asks only for data required by the first user journey. Consent, age, and region checks appear before sensitive questions.
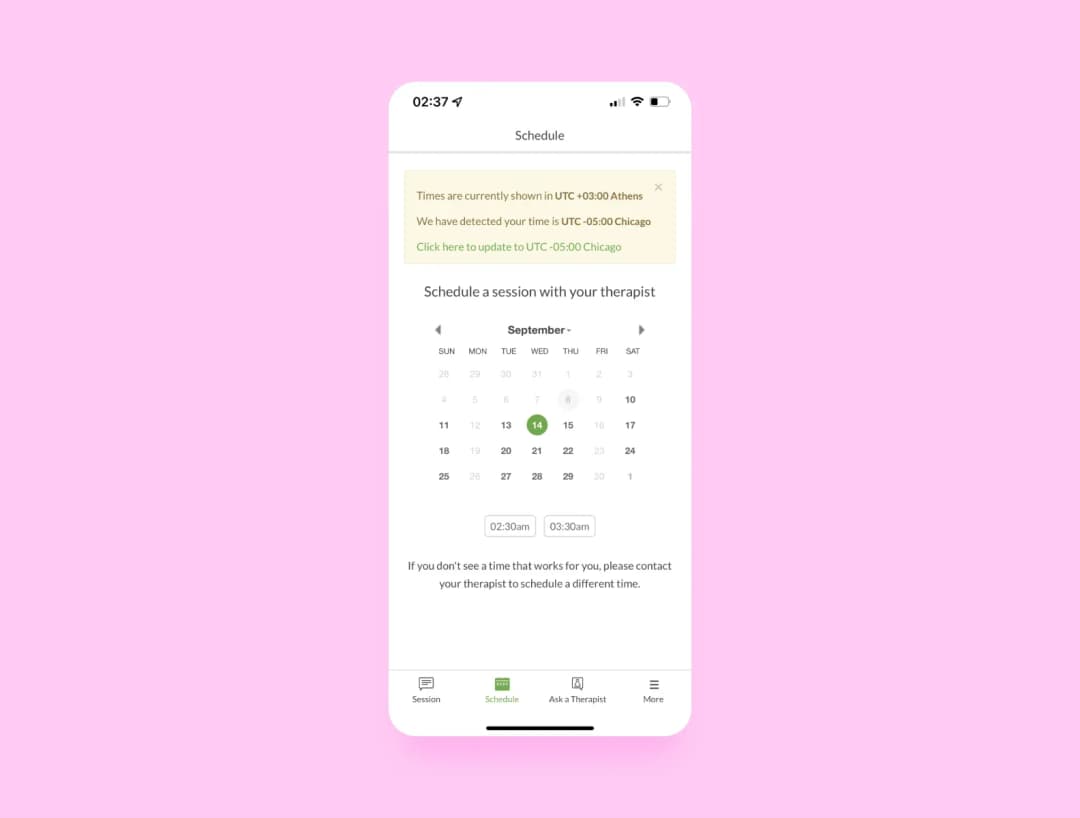
Teletherapy apps need searchable profiles, availability, matching, and scheduling. A profile gives users enough context to choose a professional without exposing unnecessary personal information. Clinician and admin roles also require separate permissions for notes, schedules, and client records.
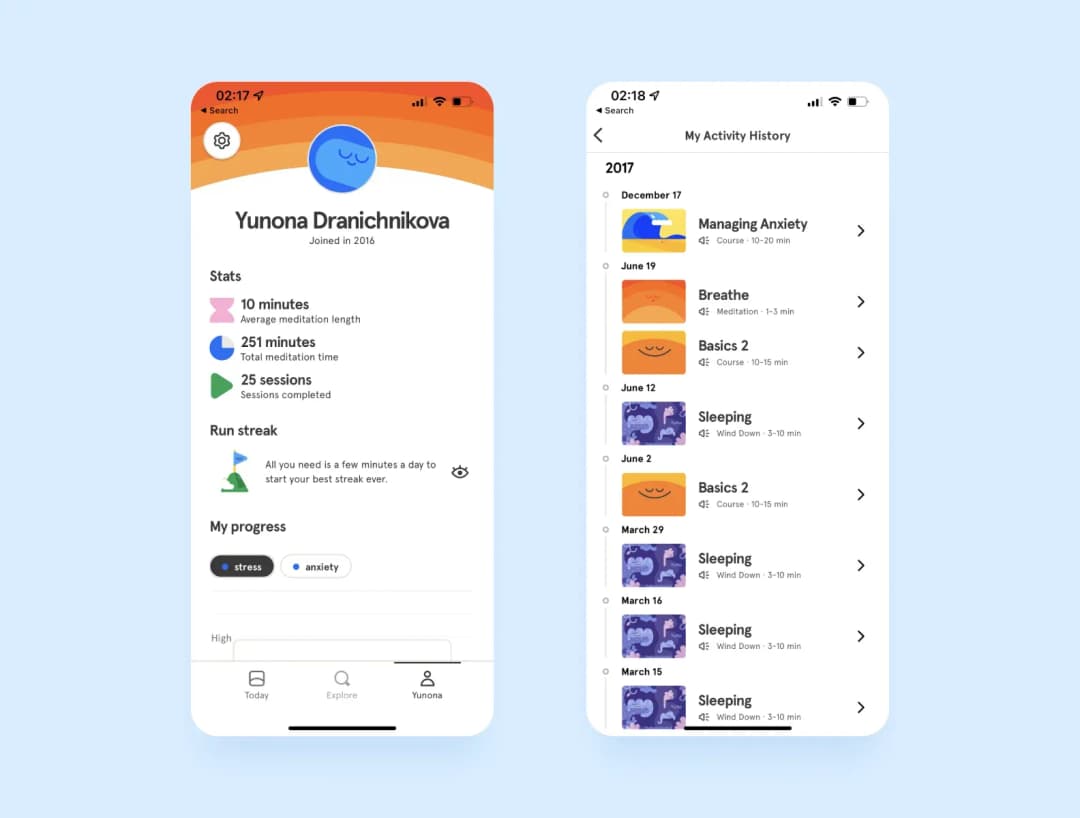
Mood entries, journals, assessments, and goals create longitudinal value when they help users notice patterns. The dashboard needs to explain what changed without presenting a diagnosis. Export and sharing controls also let users decide whether a professional receives the history.
Notifications work when users control their timing, frequency, and content. Session reminders and optional check-ins support the main flow without exposing sensitive details on a lock screen. Captions, readable contrast, screen reader labels, and plain language make the same flow usable for more people.
We designed and developed My Therapy Assistant, a UK online psychotherapy service for mobile and web. Patients manage sessions, notes, materials, and goals. Therapists work with schedules and client records, while admins review profiles.
Three roles expanded the product to about 100 screens. Users also needed notes without leaving a live call.
We created window management that minimizes video while other tools stay open. Read the online therapy app case study.
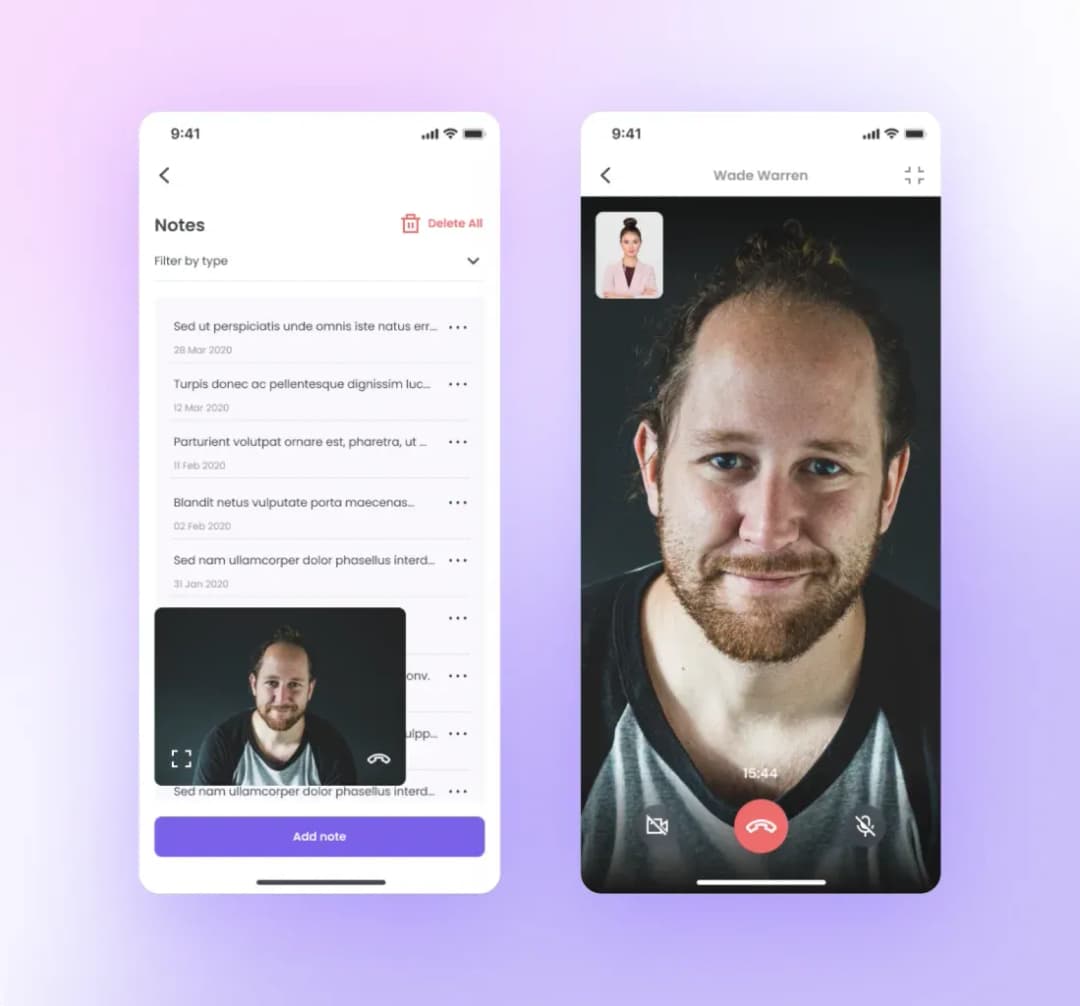
Teletherapy products often combine text, audio, and video so users can choose an appropriate session format. Product teams still need vendor assessment, encryption, failure handling, and clear recording rules. A dropped call or unavailable provider also needs a safe fallback rather than a dead end.
Mental health apps need a compliance model before development begins. The rules depend on who operates the app, what data it collects, and whether it works with a healthcare provider.
The Health Insurance Portability and Accountability Act (HIPAA) covers US covered entities and business associates. The General Data Protection Regulation (GDPR) covers EU personal data processing. The FTC Act and Health Breach Notification Rule can cover consumer apps outside HIPAA.
| Trigger | What to clarify | Product requirement |
| App works for a US covered provider | Does the vendor handle protected health information? | BAA, access controls, encryption, logs |
| App processes EU personal data | What is the lawful basis and transfer model? | Consent, user rights, transfer records |
| Consumer app sits outside HIPAA | Does it combine identifiable health data? | HBNR review, breach plan, accurate claims |
| AI gives mental health guidance | Is output clinical or crisis-related? | Human review, limits, testing, escalation |
| App connects EHRs, wearables, video, analytics, or ads | Who receives sensitive data? | Vendor review, permissions, retention |
Compliance is an architecture input. Teams map operators, users, jurisdictions, and data flows before selecting vendors. This keeps medical software development aligned with risk. The FTC’s first Health Breach Notification Rule actions involving health apps show why products outside HIPAA still need federal privacy review.
Teams choose the stack after defining the product model, data flows, and compliance scope. React Native, Flutter, or a cloud provider does not make an app HIPAA-compliant by itself. The architecture also needs to support accessibility, auditability, integrations, and reliable failure handling.
A good mental health app design starts with the user flow, not a vendor list. The features of mental health apps determine whether the mental health software needs a chatbot, wearable technology, or electronic health records.
Artificial intelligence can support summaries or recommendations, but safety testing and human review remain product requirements. This makes architecture part of mental health application development rather than a separate infrastructure task.
| Layer | Practical options | Selection criteria |
| Mobile client | React Native, Flutter, native iOS or Android | Accessibility, device access, team expertise |
| Backend and API | Node.js with NestJS, Python frameworks | Auditability, real-time load, ML requirements |
| Data | PostgreSQL, encrypted object storage | Retention, encryption, residency, recovery |
| Real-time care | WebRTC or assessed chat and video SDKs | BAA availability, encryption, recording policy |
| Cloud operations | AWS, Azure, or GCP eligible services | Contracts, logging, key management, recovery |
| Integrations | FHIR or HL7 EHR APIs, wearables, payments | Consent, permissions, vendor risk, fallback behavior |
| AI layer | Assessed NLP or LLM provider, in-house model | Privacy, human review, safety evaluation, crisis controls |
The hardest problems appear when clinical safety, privacy, usability, and scope pull the team in different directions. Each mitigation needs a product decision rather than more functionality.
| Challenge | Why it fails | Mitigation |
| Trust and retention | Generic rewards feel manipulative | User-controlled frequency and meaningful feedback |
| Clinical safety | Guidance crosses into diagnosis or crisis care | Expert review, claim limits, escalation |
| Privacy and personalization | Personalization requires more sensitive data | Minimize data, separate consent, deletion and export |
| Accessibility and emotional load | Dense interfaces deter vulnerable users | Plain language, calm patterns, assistive testing |
| Interoperability | Vendors fail or expose data | Standards, vendor review, retry and fallback flows |
| Scope inflation | Teams combine too many product categories | One user job, validated MVP, then expansion |
Onboarding questions improve relevance when they change the experience. Users still need control over reminders, recommendations, and rewards.
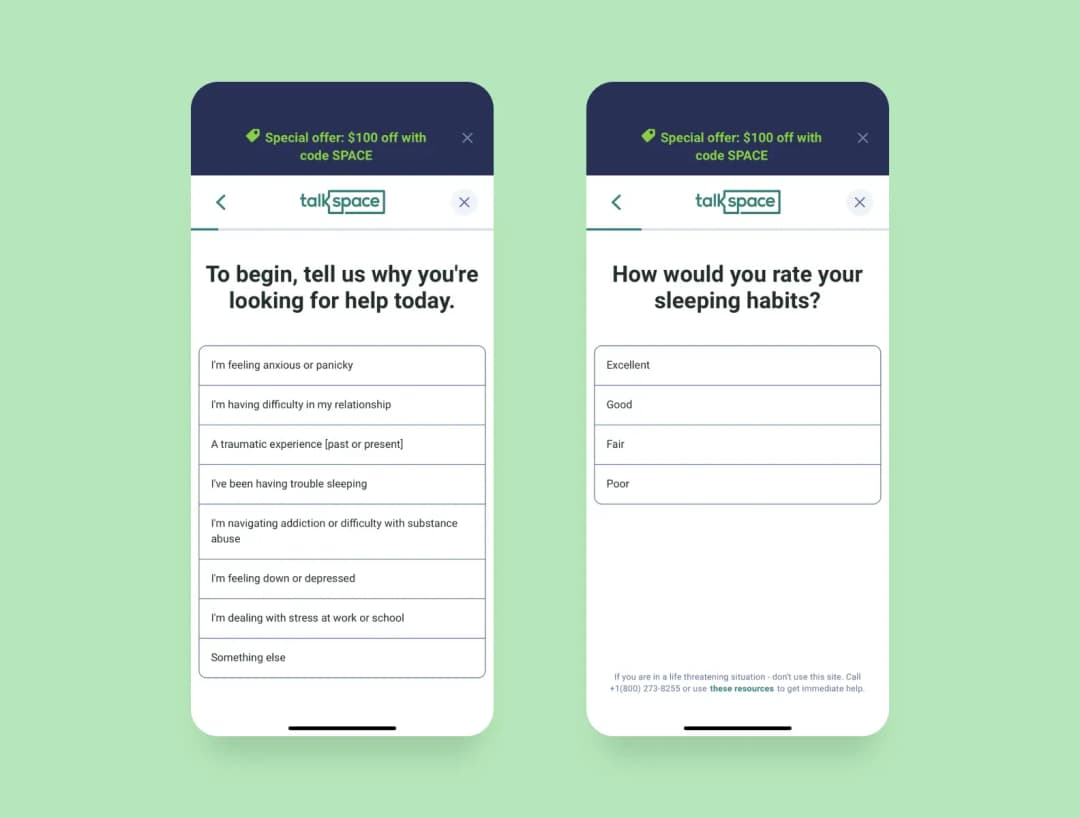
Integration problems deserve special attention because they happen between systems that work correctly on their own. A video vendor can lose regional coverage, an EHR can return incomplete data, or an analytics tool can collect more than the consent model allows.
Teams reduce this risk by documenting ownership, testing failure states, and keeping a fallback for every critical dependency. The same discipline limits scope because each new integration adds another contract, data flow, and recovery path. That is where integration planning matters.
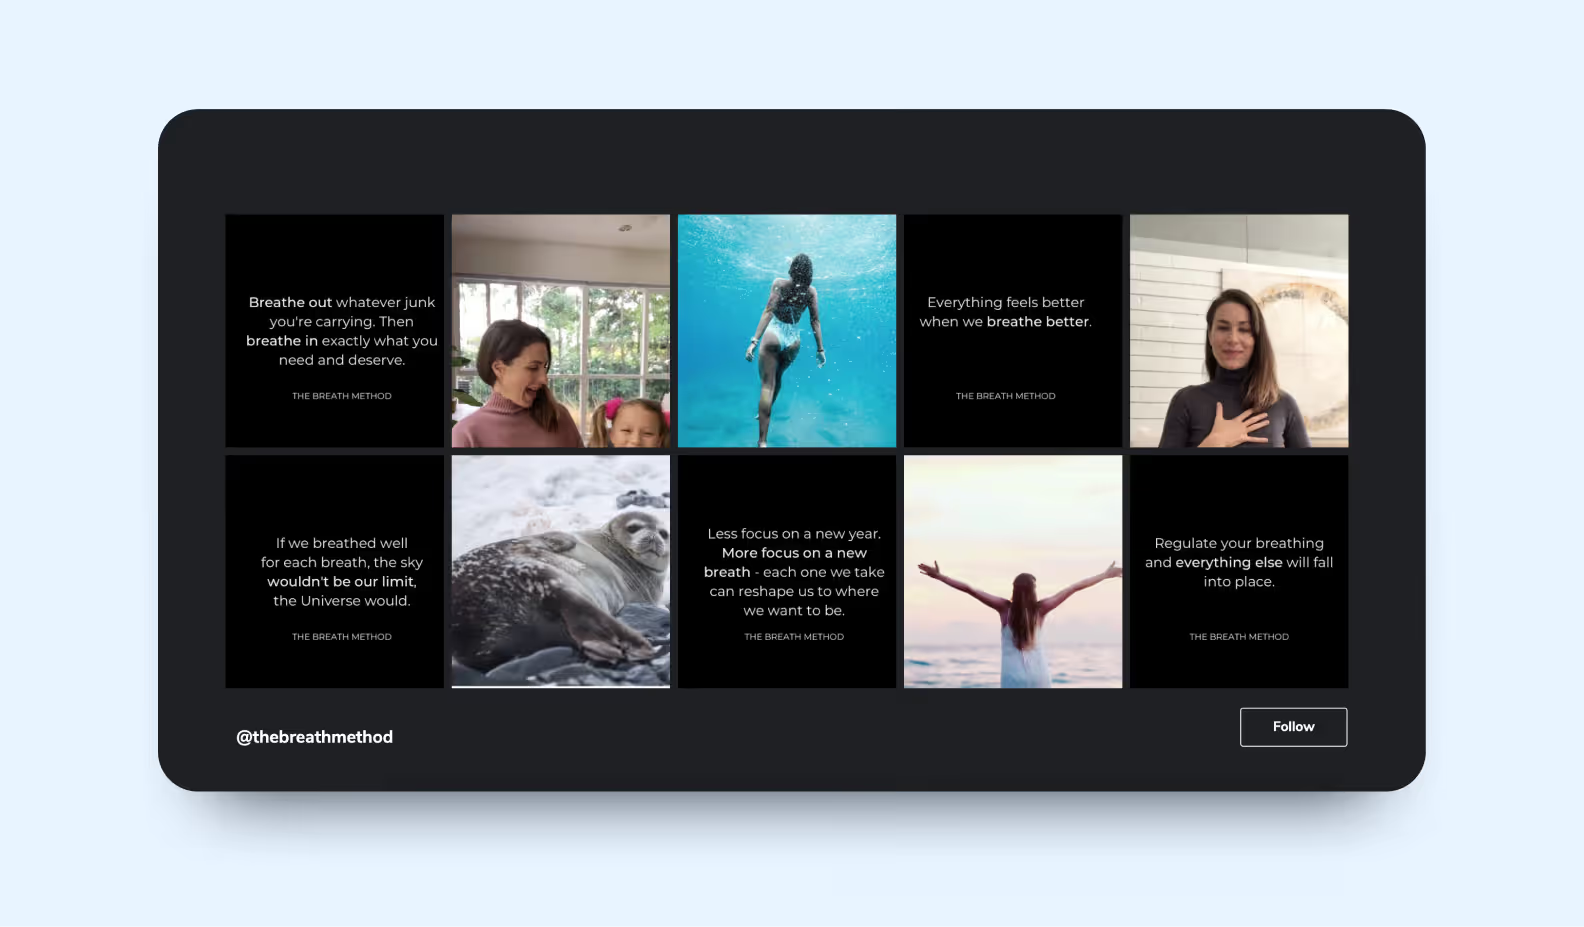
We built Breathmethod, a meditation app with breathing content and mental health support. Its launch also needed a landing page that displayed recent Instagram posts automatically.
The Gatsby plugin exposed post data but did not create the required feed. We added sorting for the ten latest posts, built a slider, connected Netlify, and scheduled daily refreshes through Zapier.
The result connected product content with marketing. Read the Breathmethod case context.
Purrweb’s healthcare app development cost guide was updated in 2026. Mental health and meditation apps typically fall in the $60,000–$120,000 range. The final budget depends on scope, integrations, security, team rates, and post-launch support.
The estimate below describes one Purrweb project scope rather than a universal market quote. It assumes discovery, UI/UX design, development, quality assurance, and project management for a mobile product. Advanced video, EHR connectivity, AI, or additional compliance work can change both cost and timeline.
Illustrative Purrweb estimate for the listed scope
| Stage | Work | Estimated hours | Estimated schedule | Approximate cost |
| Initial meeting | Discuss the product idea | 1 day | 1 day | No cost |
| UI/UX design | Map journeys and design screens | 160 hours | 6 weeks | $8,010 |
| Development | Build the application | 1,018 hours | 9 weeks | $45,810 |
| QA | Test flows and resolve defects | 270 hours | Runs with development | $5,400 |
| Project management | Coordinate delivery and communication | Runs with project | 15 weeks | $4,050 |
| Total | Listed project scope | Not applicable | About 4 months | $63,270 |
A useful development process resolves product risk before the team commits to a broad feature set. The four steps below connect the user problem, compliance, architecture, and launch validation without turning the MVP into a full care ecosystem.
Mental health app developers use discovery to make the app boundary testable before product development begins. This reduces development costs and helps a team compare development services against the actual scope of the mental health solution. Teams define mental health goals and measurable health outcomes with mental health experts before they build mental health interventions.
Choose the primary user job, app type, target regions, and clinical claims. Map which health data enters the product, where it moves, who can access it, and which rules apply. These decisions shape the feature boundary and compliance scope.
Research the target users and involve mental health professionals where the product makes care-related claims. Prototype critical flows, test language and accessibility, and keep the MVP focused on one outcome. Validation should include crisis paths and consent, not only the happy path.
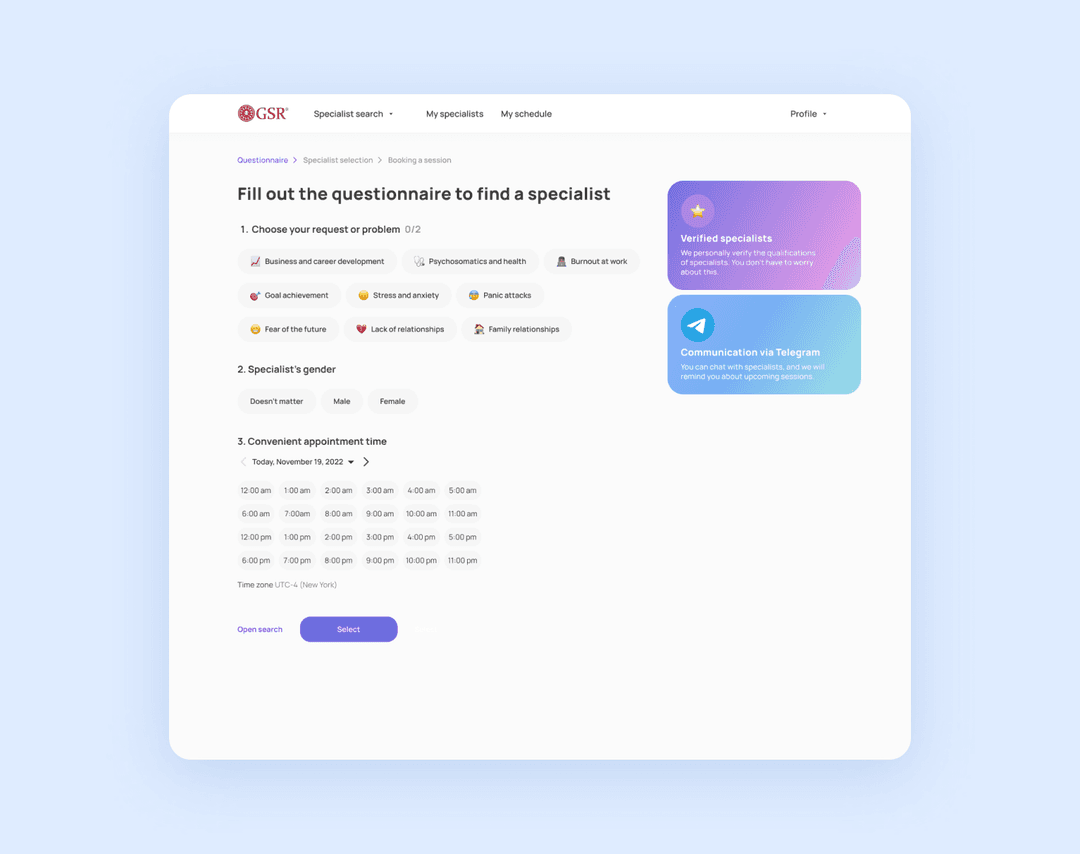
We built an MVP platform for finding GSR specialists and booking online consultations. It needed separate client and specialist journeys without making the first release too broad to test.
We mapped both flows, created a reusable UI kit, and added a questionnaire that narrowed the specialist catalog before search and booking.
The focused scope kept secondary features out of the first release. The team delivered the MVP in four months within the planned $40,000 budget. Read the GSR platform case.
Implement the client, backend, data controls, and core flows around the approved architecture. Test permissions, vendor failures, offline states, and integrations before launch. Monitoring and audit logs need clear ownership from the start.
Run functional, security, accessibility, and safety checks before a gradual release. After launch, monitor product outcomes, incidents, support requests, and failure patterns. The next feature follows evidence from real use rather than the original wish list.
The three case callouts above show how mental health products create different delivery constraints. Breathmethod needed a reliable content integration. My Therapy Assistant required role-specific therapy workflows. The GSR platform kept its first release focused enough to test demand.
Together, the cases cover self-guided support, teletherapy, and specialist matching without repeating one product model.
A mental health product becomes easier to estimate once the team defines its care model and data boundary. Those choices narrow the MVP, expose compliance work, and show which integrations deserve early testing. They also prevent a self-guided app from inheriting the cost and operational burden of a teletherapy platform without a clear reason.
The next useful step is a scoped product workshop that maps the first user journey, sensitive data, and launch assumptions. This gives design and development teams a concrete basis for the estimate.
➡️ Planning a mental health product? Tell Purrweb what you are building and get a project estimate within 48 hours.
According to Purrweb’s healthcare cost guide updated in 2026, mental health and meditation apps typically cost $60,000–$120,000. A focused self-guided product may sit near the lower end. Teletherapy, AI, EHR integrations, video, and advanced compliance controls increase the budget.
The final estimate should state the platforms, feature scope, integrations, security requirements, team rates, and post-launch support.
Most mental health apps need secure onboarding and consent, one primary support flow, progress feedback, and notifications. They also need privacy controls, accessibility, and crisis resources. The support flow could provide mood tracking or guided interventions.
Teletherapy apps also require provider profiles, matching, scheduling, secure communication, payments, and role-based clinician workflows. The MVP should focus on one primary user job rather than combine every category.
Not every mental health app is automatically subject to HIPAA. It generally applies when a US covered entity or business associate handles protected health information.
Independent consumer apps may fall outside HIPAA. They can still be covered by the FTC Act, the Health Breach Notification Rule, state privacy laws, or GDPR. Map the operator, users, data flows, and jurisdictions before development.
A focused MVP often takes about four months, but the timeline changes with product scope and risk. Discovery, compliance planning, UX research, integrations, accessibility testing, security review, and launch validation all affect delivery.
A self-guided wellness app is usually faster than a teletherapy platform with clinician workflows, video, payments, EHR connectivity, and regulated health data.
Common models include subscriptions for guided content and tracking, per-session payments, marketplace commissions, and freemium access with premium modules. B2B contracts with employers, insurers, or healthcare providers are another option.
The model should match the app’s value cycle and trust expectations. Advertising based on sensitive health data can create significant privacy and reputation risks.
A typical stack may use React Native or Flutter for the client, Node.js or Python for backend services, PostgreSQL, and encrypted object storage. Secure communication may rely on WebRTC or an assessed SDK. EHR integrations commonly use FHIR or HL7 APIs.
The right stack depends on data sensitivity, integrations, accessibility, scale, vendor contracts, and the team’s ability to operate it securely.
Mental health apps generate revenue through subscriptions, paid sessions, marketplace commissions, employer contracts, provider licensing, or insurer partnerships. Large products often combine B2C and B2B channels. A new app should validate one model first.
Revenue quality depends on retention, clinical or practical value, trust, and sustainable service delivery. Copying a competitor’s price does not create those conditions.
Mental health apps can be profitable when the product solves one clear user problem, earns trust, and matches its monetization model to the care journey. Revenue may come from subscriptions, session fees, commissions, or B2B contracts.
Profitability still depends on acquisition cost, retention, clinician supply, compliance expense, and whether users see measurable value.
AI can support journaling prompts, content discovery, summaries, triage support, and personalization. It should not be treated as an unsupervised replacement for licensed care or emergency support.
Safe implementation requires clear limits, privacy controls, expert-reviewed content, red-flag escalation, and human oversight for high-risk cases. Teams also need continuous testing for inaccurate or harmful outputs.


